
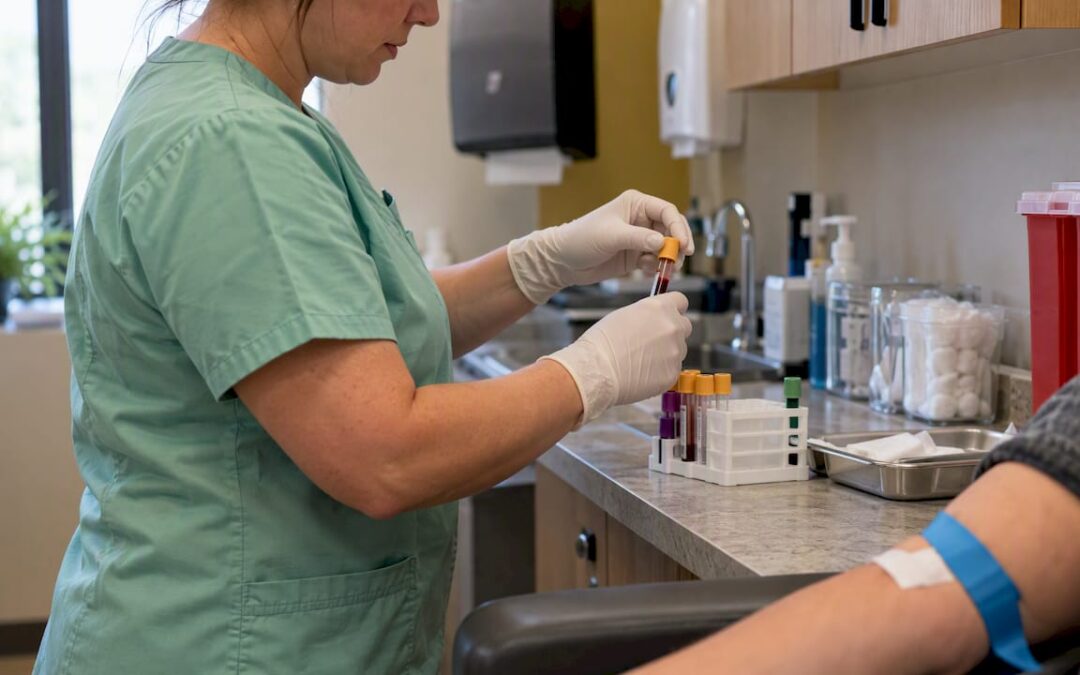
Bone turnover markers are blood or urine tests that show how quickly bone is being broken down or rebuilt, and their clearest clinical use today is monitoring treatment response and adherence. PINP and β-CTX-I serve as the reference markers for this purpose. Both carry real limitations: day-to-day biological variability and chronic kidney disease can distort results enough to mislead a clinician who reads a single value in isolation.
TL;DR:
- Bone turnover markers fluctuate with biological rhythms and kidney function, requiring consistent timing, fasting, and the same assay platform for reliable interpretation.
- PINP and β-CTX-I are the primary reference markers for osteoporosis and treatment monitoring, with alternatives like BALP or TRACP5b suited for patients with kidney disease.
- Changes in bone turnover markers within 26% (least significant change) at three months indicate treatment response or adherence, but isolated values are less informative.
- Elevated markers modestly increase fracture risk prediction but are not diagnostic on their own and should complement imaging and clinical assessment.
- Variability and confounders mean bone turnover markers are best used to track treatment response over time rather than diagnose osteoporosis.
Table of Contents
- Why bone remodeling produces measurable markers
- Formation versus resorption markers and what each one tells you
- How labs measure bone turnover markers and why handling matters
- What the evidence shows about using bone turnover markers clinically
- Interpreting a result: least significant change and confounders
- Practical ordering: when to test and what to put on the request
- Where bone turnover markers fall short
- How bone turnover markers fit a clinic-based bone program
- What matters most if you only remember one thing
- A complementary approach: supervised osteogenic loading
- FAQ
- Sources
Why bone remodeling produces measurable markers
Bone is never static. Osteoclasts resorb old bone matrix while osteoblasts lay down new matrix in a coupled cycle that continues throughout life, accelerating after menopause or with certain medications and slowing with age-related decline in remodeling capacity. Each phase of that cycle releases distinct byproducts into circulation: collagen fragments during resorption, enzymes and peptides during formation. Bone turnover markers capture these byproducts in blood or urine, giving a biochemical snapshot of whatever is happening at the cellular level right now.
That immediacy is the entire point. Dual-energy X-ray absorptiometry measures bone mineral density, which changes slowly, often requiring one to two years to show a meaningful shift after starting or stopping therapy. Bone turnover markers can move within weeks, according to a 2025 consensus paper from the International Osteoporosis Foundation, the International Federation of Clinical Chemistry and Laboratory Medicine, and the European Society for Clinical and Economic Aspects of Osteoporosis and Osteoarthritis. The consensus describes bone turnover markers as providing dynamic, near-term information on bone metabolism, in contrast with bone mineral density’s slow trajectory.
This speed makes bone turnover markers useful well beyond routine osteoporosis management. They help track:
- Paget disease activity, where bone alkaline phosphatase often tracks disease flares and treatment response.
- Osteomalacia, where formation markers can signal impaired mineralization alongside vitamin D studies.
- Chronic kidney disease associated bone disorder, where renal clearance complicates which marker to trust.
- Early post-fracture healing, where resorption markers rise transiently and can confound interpretation if testing is mistimed.
Each of these contexts demands a different marker or a different interpretation of the same marker, which is why a one-size-fits-all approach to bone turnover testing rarely works in practice.
Formation versus resorption markers and what each one tells you
Clinicians generally split bone turnover markers into two families: formation markers, which reflect osteoblast activity, and resorption markers, which reflect osteoclast activity. Knowing which family a marker belongs to, and its specific quirks, determines whether a result is trustworthy.
Procollagen type I N-terminal propeptide (PINP) comes in two forms. Intact PINP is cleared by the liver and stays relatively stable in renal impairment, while total PINP is partly cleared by the kidney and can accumulate in reduced renal function. That distinction matters most in older patients or anyone with reduced kidney function, where total PINP results can look falsely elevated.
β-C-terminal telopeptide of type I collagen (β-CTX-I, often just called CTX) is the standard resorption marker. It is sensitive to food intake and circadian rhythm, dropping after meals and peaking overnight, which is why fasting morning draws are standard practice rather than a minor preference.
Other markers fill specific niches:
- Bone-specific alkaline phosphatase (BALP) is a formation marker that is not really cleared, making it a reasonable substitute for PINP in kidney disease.
- Osteocalcin reflects osteoblast activity but is more variable and less standardized across laboratories than PINP.
- N-terminal telopeptide (NTX), a urinary or serum resorption marker, was historically popular but has largely been supplanted by CTX in reference guidelines.
- Tartrate-resistant acid phosphatase 5b (TRACP5b) is a resorption marker produced by osteoclasts themselves rather than derived from collagen breakdown, and it is not affected by renal clearance, which makes it valuable in chronic kidney disease.
IOF, IFCC, and ESCEO reaffirm serum or plasma total PINP and plasma β-CTX-I as the reference bone turnover markers for osteoporosis in patients with normal kidney function, while recommending BALP and TRACP5b for patients with chronic kidney disease associated osteoporosis, since tPINP and β-CTX-I may accumulate in that population. For routine practice in a patient with preserved renal function, pairing PINP with β-CTX-I covers both sides of the remodeling cycle without requiring a larger panel.
How labs measure bone turnover markers and why handling matters
Most bone turnover markers are measured using enzyme-linked immunosorbent assays or automated chemiluminescence and electrochemiluminescence immunoassays. Platform choice affects comparability: results from one manufacturer’s automated assay are not necessarily interchangeable with another’s ELISA, even when both claim to measure the same marker, which is why trend monitoring should stay within the same lab and assay whenever possible.

Pre-analytical handling is where most real-world variability creeps in, and it is also the easiest problem to fix. The National Bone Health Alliance recommends collecting CTX consistently as a morning fasting draw in EDTA plasma, since CTX is sensitive to both circadian rhythm and recent food intake. PINP is far less affected by timing or fasting status, giving it more flexibility for sample collection.
Before ordering or interpreting a bone turnover marker panel, document:
- Current and recent medications, including bisphosphonates, denosumab, teriparatide, and glucocorticoids.
- Any fracture within the past twelve months, which transiently elevates resorption markers.
- Recent vigorous exercise, which can acutely raise turnover marker levels.
- Menstrual cycle phase in premenopausal patients, since estrogen fluctuation affects remodeling rate.
- The specific lab and assay platform used previously, so follow-up draws match.
Pro Tip: Ask your lab to report the assay manufacturer and, where available, the least significant change for that assay, since this turns a single number into a result you can actually act on.
What the evidence shows about using bone turnover markers clinically
Bone turnover markers serve two evidence-backed roles: flagging fracture risk at a population level and tracking individual treatment response. The two roles are not interchangeable, and conflating them is a common source of clinical confusion.
On fracture risk, meta-analyses summarized in a clinical algorithm for biochemical markers found that higher baseline PINP and β-CTX-I are associated with a modestly increased fracture risk, with a gradient of risk per standard deviation increase of roughly 1.2 to 1.3 after adjustment for other factors in some studies. That association is real but modest. Bone turnover markers add only a small amount of predictive power on top of bone mineral density and standard clinical risk factors, so they are not a substitute for a fracture risk assessment built on DXA and clinical history.
Meta-analyses link elevated PINP and β-CTX-I to a modest increase in fracture risk per standard deviation in some adjusted models, supporting the use of bone turnover markers as one input among several rather than a standalone predictor, according to the same algorithm review.
Monitoring therapy is where bone turnover markers earn their keep. The TRIO study and related trial data, summarized in the same algorithm paper, found that three months of bisphosphonate therapy suppressed PINP and β-CTX-I beyond the least significant change in a majority of treated women, and measuring both markers together increased the detection rate compared with checking either one alone. In practical terms, this means:
- A meaningful drop in PINP and β-CTX-I at three months supports adherence and early biologic response.
- A lack of suppression beyond the least significant change should prompt a conversation about adherence, absorption, or an alternative diagnosis.
- Bone turnover markers are not diagnostic tools on their own; a single elevated or low value never confirms or rules out osteoporosis.
Interpreting a result: least significant change and confounders
A single bone turnover marker value means little without context. The least significant change, or LSC, defines how much a result must move between two draws to represent a true biological change rather than normal assay and biological noise. The standard formula is LSC equals 2.77 multiplied by the assay’s intra-individual coefficient of variation. For a CTX assay with an intra-individual coefficient of variation of 9.4%, the resulting LSC is about 26%, meaning a change smaller than that could simply be noise.
Controllable factors, like fasting status and draw timing, should be standardized and documented at every visit. Uncontrollable factors, like age, sex, and menopausal status, shift baseline turnover rates and should be noted in the chart rather than treated as confounders to eliminate.
Chronic kidney disease deserves its own line of reasoning. Total PINP and β-CTX-I accumulate as renal clearance falls, producing falsely elevated readings that have nothing to do with actual bone turnover. In patients with advanced chronic kidney disease, intact PINP, BALP, and TRACP5b are the preferred markers, since none of the three depends heavily on renal clearance. Whichever markers are chosen, trends on the same assay over time are far more informative than any single value.
Practical ordering: when to test and what to put on the request
A workable testing sequence looks like this:
- Order a baseline PINP and β-CTX-I before starting antiresorptive or anabolic therapy.
- Repeat testing around three months for oral bisphosphonates, adjusting timing for agents with different pharmacokinetics.
- Space subsequent retests at intervals tied to the therapy and clinical question, such as annually once a stable response is confirmed.
- Schedule the draw as a fasting morning sample, especially for CTX, and keep the time of day consistent across visits.
- Note the assay manufacturer, specimen type, and any recent fracture or medication change directly on the lab request.
Reports should include the assay name, specimen type, and a reference range specific to that assay, since reference intervals are not interchangeable across platforms.
Where bone turnover markers fall short
Analytical and biological variability limits what a single bone turnover marker value can tell you, which is why guidelines favor trends over snapshots. There is still no universal consensus on specific treatment targets for suppression, and guideline uptake remains inconsistent across specialties. Data in chronic kidney disease populations remain limited, and bone turnover markers are not yet well integrated into long-term fracture prediction tools. Laboratory harmonization, clinician familiarity, and reimbursement gaps all slow broader adoption.
How bone turnover markers fit a clinic-based bone program
Biochemical signals from bone turnover markers can complement, rather than replace, the structural tracking that DXA scans and clinic-delivered osteogenic loading programs already rely on. Clinical monitoring through imaging and physician oversight remains essential. Used appropriately, bone turnover markers offer an earlier biochemical hint of remodeling activity between the longer intervals typical of bone density scans.
What matters most if you only remember one thing
The single most useful habit in bone turnover marker testing is consistency: same lab, same assay, same time of day, same fasting status, every single time. Clinicians tend to over-trust an isolated elevated or low value and under-trust a well-documented trend, which is backward given how much biological noise these assays carry.
The conventional advice to “check bone markers” without specifying PINP and β-CTX-I as the reference pair, without accounting for renal function, and without calculating a least significant change, sets patients up for confusing or contradictory results. Chronic kidney disease is the most common blind spot: ordering total PINP or standard CTX in a patient with reduced kidney function and interpreting the elevated result as worsening bone loss is a mistake that happens more often than it should.
If you take one thing from the evidence here, let it be this: bone turnover markers answer the question “is this treatment working right now,” not “does this patient have osteoporosis.” Reserve them for that job, pair them with DXA rather than instead of it, and in kidney disease switch to BALP, intact PINP, or TRACP5b before trusting a number.
— Aaron
A complementary approach: supervised osteogenic loading
We run supervised osteogenic loading sessions once a week, a brief, low-impact protocol designed to stimulate bone-building response without medication. Our sessions are meant to sit alongside guideline-based therapy and clinician-ordered monitoring, including DXA and bone turnover marker testing, not replace either one. If you want to talk through how a clinic-based program fits your current bone health plan, reach out through our Rancho Cordova location to schedule a visit.
FAQ
What is the one vitamin that rebuilds bone density?
No single vitamin rebuilds bone density on its own, and claims suggesting otherwise oversimplify how bone metabolism works. Vitamin D supports calcium absorption and plays a supporting role in bone health, but adequate bone rebuilding depends on a combination of nutrition, mechanical loading, hormonal status, and, where indicated, prescribed therapy.
What is a good CTX score?
There is no single universal “good” CTX value, since reference ranges differ by assay, lab, age, and sex, and results should be interpreted as fasting morning draws in EDTA plasma per standard recommendations. A result is best judged against your own prior values using the least significant change for that specific assay, rather than against a generic cutoff.
What is a bad number for osteoporosis?
Osteoporosis diagnosis relies primarily on bone mineral density from a DXA scan, not on a bone turnover marker value, so there is no single “bad number” for a marker alone. Elevated PINP or β-CTX-I can suggest higher bone turnover and a modestly increased fracture risk gradient per standard deviation, but these markers support a diagnosis made with imaging rather than replace it.
What does a high bone turnover rate mean?
A high bone turnover rate, reflected in elevated formation and resorption markers, generally means bone is being broken down and rebuilt faster than typical for your age and sex, which can accompany menopause, certain medications, or conditions like Paget disease. On its own, a high result does not diagnose a specific condition. It should be interpreted alongside DXA results, clinical history, and, where relevant, kidney function.
Sources
- Update on the role of bone turnover markers in the diagnosis and management of osteoporosis: a consensus paper
- Update on the role of bone turnover markers in the diagnosis and management of osteoporosis: a consensus paper (Springer)
- Use of CTX-I and PINP as bone turnover markers: National Bone Health Alliance recommendations